Pilär cystor
Epidermoid and sebaceous cysts
Granskad av Dr Toni Hazell, FRCGPSenast uppdaterad av Dr Philippa Vincent, MRCGPSenast uppdaterad 20 Nov 2021
Uppfyller patientens redaktionella riktlinjer
- Ladda nerLadda ner
- Dela
- Language
- Diskussion
- Ask Patient
- Ljudversion
- Lägg till i föredragna källor på Google
Medicinska yrkesverksamma
Professionella referensartiklar är utformade för att användas av vårdpersonal. De är skrivna av brittiska läkare och baserade på forskningsbevis, brittiska och europeiska riktlinjer. Du kan hitta Epidermoida och pilarcystor artikel mer användbar, eller en av våra andra hälsoartiklar.
What are epidermoid and pilar cysts?
Epidermoid or pilar cysts are very common and are usually of no clinical significance.
Epidermoid cysts (also known as epithelial, epidermal or sebaceous cysts) are intradermal or subcutaneous tumours. Epidermoid cysts may occur anywhere on the body but occur most often on the face, scalp, neck, back and scrotum. Although they are most commonly known as sebaceous cysts, they actually do not involve the sebaceous gland.1
Pilar cysts (also called trichilemmal cysts) are clinically indistinguishable from epidermal cysts. They contain keratinous material, are often multiple and there may be an autosomal dominant inheritance.2
Who gets epidermoid and pilar cysts? (Epidemiology)2
Pilar cysts and epidermoid cysts are most common types of skin cyst.
They are usually sporadic but can occur as part of an autosomal dominant trait.
They are more common in women than men.
They are very slow growing.
Epidermoid cysts are also usually sporadic but can occur as part of an autosomal dominant trait.
They tend to occur between the ages of 20 and 40 and are twice as common in men than women.
Babies often develop tiny epidermoid cysts, which spontaneously resolve, called milia, colloquially known as "baby acne" or "milk spots" (though neither of these names is accurate).
Up to 1% of epidermoid cysts have been shown to transform to squamous cell carcinoma or basal cell carcinoma.
Immunosuppressants such as imiquimod and cyclosporine have been shown to cause epidermoid cysts.
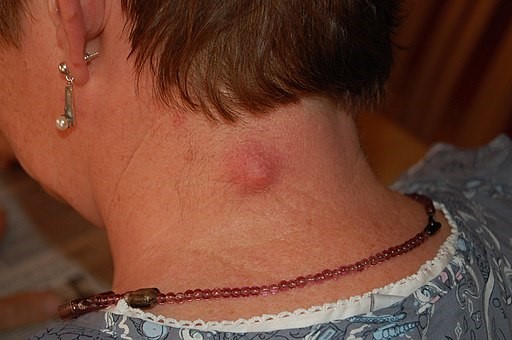
Epidermoid cyst on the neck
Epidermoid and pilar cyst symptoms
Most often they present as a painless skin lump.
They may present with discharge of an offensive thick creamy material.
If they become infected, they are red, inflamed and painful.
Lesions of the genitals can be painful during intercourse and cause problems with walking or wearing underwear. They can also interfere with micturition.
Epidermoid and pilar cysts appear as firm, round, mobile, flesh-coloured to yellow or white subcutaneous nodules of variable size.
A central pore or punctum may tether the cyst to the overlying epidermis and a thick cheesy material can sometimes be expressed.
In people with dark skin, the cysts may also be pigmented.
Sites affected by epidermoid and pilar cysts
The sites most commonly affected are, in descending order of frequency, the face, the trunk, the neck, the extremities and the scalp.
Cysts of the genitals are less common and may appear as a mass in the vulva, the clitoris, the penis, the scrotum, or the perineum. In cultures which practise female circumcision (or female genital mutilation) cysts on the vulva are common.
The ocular and oral mucosae can also be affected and cysts have been reported on the palpebral conjunctivae, on the lips, on the buccal mucosa, on and under the tongue and even on the uvula. These are not sites with hair follicles.
Cysts may occur on the extremities. Subungual cysts can cause changes in the nails, such as onycholysis and subungual hyperkeratosis, which may be mistaken for psoriasis or onychomycosis. These cysts also produce changes in the nails (such as pincer nails) erythema, oedema, tenderness and pain.
Palmoplantar lesions represent a unique subset of epidermoid cysts.
Differentialdiagnos
Other causes of skin cysts.
A lipoma tends to be larger and is very soft.
A neurofibroma is hard and may be multiple.
An abscess is hot and red and may resemble an infected sebaceous cyst.
A Merkel's cell carcinoma may look like a pilar or epidermoid cyst but occurs in older people and tends to be very fast growing.
Multiple cysts in a teenager may suggest Gardner's syndrome.
Diagnosing epidermoid and pilar cysts (investigations)
Usually the diagnosis is clear and no investigations are required. If malignancy is suspected, excision and histology are required.
Associerade sjukdomar
Epidermoid cysts are a feature of Gardner's syndrome which is an autosomal dominant condition comprising familial polyposis coli, cutaneous cysts and osteomas or other soft-tissue tumours. The cysts tend to occur at an earlier age than usual (presenting most often in the early teenage years). The face may be involved but the extremities tend to be affected more than the trunk.
Epidermoid and pilar cyst treatment
Most people with an epidermoid or pilar cyst do not need medical attention.
If a cyst is uncomplicated then no treatment is usually advised. The cyst may disappear spontaneously, leaving no trace. Even the most skilful excision will leave a permanent scar.
An infected cyst will usually require an oral antibiotic effective against staphylococci - for example, flucloxacillin. The infection may be mixed and, in lesions of the scalp and anogenital area, anaerobic flora are more likely.
If the cyst has ruptured, the contents can be expressed. However, the cyst may well re-form.
If the cyst is troublesome or if the patient, after counselling, is eager to have it removed then the entire cyst should be excised as a surgical procedure. However, this is usually not available on the NHS unless it is causing significant symptoms.
Excision of an epidermoid or pilar cyst
See also separate article Mindre kirurgi inom primärvården.
The usual preliminaries of informed consent are assumed.
Information includes the warning that the cyst may recur if all the wall is not removed.
Appropriate aseptic precautions should be taken.
Local anaesthetic such as 1% lidocaine with adrenaline (epinephrine) is used (note contra-indications to use of adrenaline (epinephrine) in certain areas). The area is infiltrated with local anaesthetic, being careful not to puncture the cyst.
Make a careful and superficial incision over the cyst avoiding rupture of the cyst. Care should be taken to remove all the cyst wall if the cyst is ruptured.
Toothed forceps can be used to grip the skin - a blunt dissection of adhesions allows mobilisation of the cyst and removal. A Volkmann spoon or scissors are useful for the blunt dissection.
If the cyst is large and leaves a significant defect then a resorbable subcutaneous suture should be used to close a potential space for haematoma to form.
The diagnosis of an epidermoid or pilar cyst is usually obvious. However, excised tissue should always be submitted for histology.
Complications with epidermoid or pilar cysts
Dislike of the cosmetic appearance
Infektion.
Malignant change is rare (causes rapid growth, friability and bleeding).
Prognos
They will usually grow slowly and only need removal if causing symptoms. They tend to recur if incised rather than excised.
Exklusiva uppdateringar för vårdpersonal
Håll dig informerad med de senaste kliniska uppdateringarna, professionella insikter och evidensbaserad vägledning. Patient Pro-nyhetsbrevet sammanställer viktigt innehåll för vårdpersonal—levererat direkt till din inkorg.
Genom att prenumerera accepterar du våra Sekretesspolicy. Du kan avsluta prenumerationen när som helst. Vi säljer aldrig dina uppgifter.
Vidare läsning och referenser
- Al Aboud DM, Yarrarapu SNS, Patel BC; Pilar Cyst. StatPearls, August 2021.
- Trichilemmal cyst; DermNet NZ.
- Pilar cyst; Sällskapet för dermatologi inom primärvården.
- Zito PM, Scharf R; Epidermoid Cyst.
- Al Aboud DM, Yarrarapu SNS, Patel BC; Pilar Cyst.
Om författarenVisa fullständig biografi
Uppdaterad av

Dr Philippa Vincent, MRCGP
Allmänläkare, Medicinsk Författare
MB BS, Bsc, MRCGP (2000), DCH, DFSRH, DRCOG
Dr Philippa Vincent är en NHS-läkare som arbetar i norra London.
Om recensentenVisa fullständig biografi

Dr Toni Hazell, FRCGP
MBBS, BSc, FRCGP, DFSRH, Dip GU med, DRCOG, DCH (London, UK, 2000)
Dr. Toni Hazell tog examen från St. Mary’s Hospital Medical School och genomförde sin VTS vid Northwick Park Hospital.
Artikelhistorik
Artikeln finns också på Engelska, Tyska, Spanska, Franska, Italienska, Portugisiska, Hindi, Hebreiska, Arabiska, och Svenska.
Next review due: 19 Nov 2026
20 Nov 2021 | Senaste versionen
Enkel tillgång till pålitliga behandlingar och hälsotjänster online.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.





Mer inom dermatologi
- Basalcellscancer
- Furunklar och karbunklar
- Campbell de Morgan-fläck
- Kutan larva migrans
- Ecthyma
- Genital herpes simplex
- Guinea mask sjukdom
- Henoch-Schönleins purpura
- Hereditärt angioödem
- Hidradenitis suppurativa
- Intradermala och sammansatta nevi
- Bensår
- Linjär IgA-dermatos
- Malignt melanom
- Molluscum contagiosum
- Pityriasis lichenoides
- Pomfolyx
- Postinflammatorisk hypopigmentering av huden
- Seborroisk vårta
- Zinkbrist, överskott och tillskott