Bedömning av brachialplexus och vanliga skador
Granskad av Dr Toni Hazell, FRCGPSenast uppdaterad av Dr Philippa Vincent, MRCGPSenast uppdaterad 1 Oct 2026
Uppfyller patientens redaktionella riktlinjer
- Ladda nerLadda ner
- Dela
- Language
- Diskussion
- Ask Patient
- Ljudversion
- Lägg till i föredragna källor på Google
Medicinska yrkesverksamma
Professionella referensartiklar är utformade för att användas av hälso- och sjukvårdspersonal. De är skrivna av brittiska läkare och baserade på forskningsbevis, brittiska och europeiska riktlinjer. Du kanske hittar en av våra hälsoartiklar mer användbar.
The nerve supply to the arm is from nerve roots C5-T1 via the brachial plexus. The nerves pass under the clavicle and end in the axilla.12
Brachial plexus
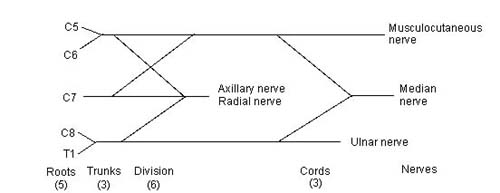
Brachial plexus injuries in adults3
Severe brachial plexus injuries cause dramatic consequences to the motor and sensory functions of the upper limb.4 Road traffic accidents have resulted in a significant increase in brachial plexus injuries.3
Milder injuries of the brachial plexus can occur, with transient symptoms and with a full recovery. Milder injuries are more common in some sports, such as martial arts, though severe brachial plexus injuries are uncommon in sports medicine.5
Epidemiologi6
Non-obstetric brachial plexus injuries are most common in young men between the ages of 15 and 25.
There is a "law of 7 70s" described by Naraka.
70% of brachial plexus injuries are due to road traffic accidents. 70% of these involve a motorcycle or a bicycle. Of these, 70% sustain multiple injuries.
70% of patients sustain a lesion of the supraclavicular plexus, of which 70% will have one or several avulsion of the plexus roots; 70% of these patients will also sustain root avulsions of the lower plexus, of whom 70% will experience chronic pain.
Ballistic trauma is the second most common cause of brachial plexus injuries in the United States.
However, a Scottish study showed that a fall from standing height was the most common mechanism of injury, suggesting that injury types are likely to vary depending on the population.7
Obstetric brachial plexus injuries are rare and decreasing in incidence due to the increasing number of Caesarean sections being performed in higher income countries.8 The incidence is reported to be 1.5 per 1000 live births in the United States9 and 0.42 per 1000 live births in the UK,10 although the risk is significantly higher in lower income countries, being reported in 14.7% of births in one Ghanian study.11 Risks of brachial plexus injuries are 100 times higher in shoulder dystocia, 14 times higher in babies who are large for gestational age and 9 times higher in forceps deliveries.12
Children born in low-resource settings are more likely both to have brachial plexus injuries and to have delayed referral for specialist management.13
Tecken och symtom6
A thorough history and examination is essential. Significant bruising and swelling may suggest vascular trauma which should be assessed by examining the radial, ulnar, and brachial pulses.
Precise examination findings depend on the injury site within the brachial plexus. Upper brachial plexus injuries can present clinically as an Erb palsy, and lower plexus injuries can present with a Klumpke palsy. C5/C6 involvement leads to paralysis of the shoulder and biceps muscles. C7 involvement leads to paralysis in extending the wrist and hand muscles. C8/T1 involvement leads to paralysis of the forearm flexors and hand intrinsic muscles.14
Examination
Se även den separata Neurologisk undersökning av de övre extremiteterna artikel.
Sensornervar
Pinch the nail base, pull the finger outwards, and ask about feeling anything. A burning feeling indicates continuity in the following nerves; absence does not necessarily mean the nerve is divided but may be due to neurapraxia instead.
Thumb - tests the median nerve supplied by C6.
Middle finger - tests the median nerve supplied by C7.
Little finger - tests the ulnar nerve suppled by C8.
Motoriska nerver
Examination can be made difficult by anomalous nerve distribution, including C4 contributing to the brachial plexus and also because many muscles are supplied by more than one motor neuron. Assessment of loss of motor function at the cervical root:
C5: shoulder movement in all directions, flexion of elbow (to some degree).
C6: flexion of elbow, rotation of forearm, flexion of wrist (to some degree).
C7: mainly a sensory trunk. (Produces generalised loss of movement in the arm, without total paralysis in any given muscle group. Always supplies the latissimus dorsi.)
C8: extension and flexion of fingers, flexion of wrist, hand movement.
T1: intrinsic muscles of the hand - eg, adduction or abduction of fingers.
Brachial plexus injuries in neonates
Obstetric palsy is classically defined as a brachial plexus injury during delivery. Caesarean delivery or being one of a multiple pregnancy is protective.12
Many cases are temporary, with full function recovering within one week (although more recent studies suggest that some neurological impairment may persist and recommend physiotherapy and occupational therapy to reduce these risks).13 However, permanent injury is not uncommon, with one study suggesting that 18.4% persisted beyond a year.15 A recent Turkish study showed that 14.3% of babies had a permanent injury.16 Se även den separata Födelseskador på barnet artikel.
There are two types of brachial plexus paralysis in neonates: upper plexus injury or Erb's palsy, and lower plexus injury or Klumpke's palsy.
Examination
Prompt evaluation and referral is recommended.13
Erbs pares (C5-C6 injury) - the arm is characteristically held adducted and internally rotated with the forearm pronated, hand and wrist flexed ('waiter's tip' position). The infant is unable to move the arm or shoulder. See the separate Erb's Palsy artikel.
Klumpke's palsy - Horners syndrom is present, ie meiosis, ptosis, anhydrosis.
Utredningar317
Plain x-rays, myelography, CT myelography, and MRI may all be indicated for the evaluation of brachial plexus. Electrodiagnostic and nerve conduction studies in association with the clinical findings can provide information regarding the location of the lesion, the severity of trauma, and expected clinical outcome.
Ledning18
Nerve damage causes a multifaceted clinical picture consisting of sensorimotor disturbances (pain, muscle atrophy, muscle weakness, secondary deformities). Brachial plexus injury may result in severe and chronic impairments for both adults and children. Therefore, early treatment and extensive rehabilitation are required. Psychological problems associated with brachial plexus injury may limit rehabilitation effects and increase disability.
Allmänna åtgärder
Adult trauma:
Rehabilitation plays an important role in reducing disability. Patients who are unable or unwilling to take part in rigorous and long-lasting physiotherapy are less likely to recover.6
Pain management is essential.19
Lower energy brachial plexus injuries are more likely to spontaneously resolve and therefore conservative management is more appropriate.
Whilst urgent surgical exploration may be required if a root avulsion or laceration injury to the plexus is suspected or in cases of open injury, retained foreign body, or vascular injury requiring vessel repair, in lower intensity brachial plexus injuries this may be delayed for 3-6 months if recovery fails to materialise.6
Obstetric trauma:
Neonatal: spontaneous recovery usually occurs and can start within days but can take months.
Occupational and physiotherapy is recommended to improve the rates of recovery. Splinting has also been shown to be of benefit.13
Other treatments include botulinum toxin injection20 although its value is debated. 13
Kirurgisk17
Specialist surgical repair in tertiary centres: options include nerve transfers, nerve grafting, muscle transfers, and neurolysis of scar around the brachial plexus.21
Phrenic nerve transfer has shown useful recovery of arm function in some patients; however, there is very little information about long-term functional and quality-of-life outcomes. There is also some evidence of consequent impairment of respiratory function. However, because patients with brachial plexus injuries are often very disabled and treatment options may be limited, the National Institute for Health and Care Excellence (NICE) recommends that phrenic nerve transfer may be considered as a treatment option.22
NICE guidance states that the evidence on the safety of free-functioning gracilis transfer to restore upper limb function in brachial plexus injury shows well-recognised complications (pain, bleeding, infection, and graft failure). However evidence on its efficacy is adequate to support the use of this procedure. This procedure should only be performed in a specialist brachial plexus unit by a multidisciplinary team including specialised physiotherapists, with input from microvascular surgeons.23
Arthrodesis of the shoulder may be considered but much more rarely in view of advances with nerve, tendon and free muscle transfers. Wrist arthrodesis may also be considered for wrist pain and gives stability to the hand.
In neonates, surgery is recommended as an early intervention, as outcome is best if repair is undertaken within six months and can be impaired if surgery is delayed until after 18 months.13
Exklusiva uppdateringar för vårdpersonal
Håll dig informerad med de senaste kliniska uppdateringarna, professionella insikter och evidensbaserad vägledning. Patient Pro-nyhetsbrevet sammanställer viktigt innehåll för vårdpersonal—levererat direkt till din inkorg.
Genom att prenumerera accepterar du våra Sekretesspolicy. Du kan avsluta prenumerationen när som helst. Vi säljer aldrig dina uppgifter.
Vidare läsning och referenser
- Orebaugh SL, Williams BA; Brachial plexus anatomy: normal and variant. ScientificWorldJournal. 2009 Apr 28;9:300-12.
- Luo TD, Levy ML, Li Z; Brachial Plexus Injuries. StatPearls, August 2021.
- Leinberry CF, Wehbe MA; Brachial plexus anatomy. Hand Clin. 2004 Feb;20(1):1-5.
- The Brachial Plexus; O Jones; Teach Me Anatomy
- Sakellariou VI, Badilas NK, Mazis GA, et al; Brachial plexus injuries in adults: evaluation and diagnostic approach. ISRN Orthop. 2014 Feb 9;2014:726103. doi: 10.1155/2014/726103. eCollection 2014.
- Brachial plexus injuries in the contact athlete: a narrative review; R Windmueller et al; Annals of Joint
- Belviso I, Palermi S, Sacco AM, et al; Brachial Plexus Injuries in Sport Medicine: Clinical Evaluation, Diagnostic Approaches, Treatment Options, and Rehabilitative Interventions. J Funct Morphol Kinesiol. 2020 Mar 30;5(2). pii: jfmk5020022. doi: 10.3390/jfmk5020022.
- Dean T, Levy ML, Luo TD, et al; Brachial Plexus Injuries.
- Traumatic brachial plexus injuries: a national review of epidemiology in the Scottish population over a 10-year period; C E Warwick and T Hems; Journal of Hand Surgery
- Epidemiology and surgical management of obstetric brachial plexus injury: a national cohort study; T A Sargut et al; Journal of Neurosurgery
- A brief overview of obstetric brachial plexus palsy; A Swift; British Journal of Midwifery
- Doumouchtsis SK, Arulkumaran S; Are all brachial plexus injuries caused by shoulder dystocia? Obstet Gynecol Surv. 2009 Sep;64(9):615-23.
- Prevalence and predisposing factors of brachial plexus birth palsy in a Regional hospital in Ghana: A five year retrospective study; C Yarfi et al; Pan African Medical Journal
- Foad SL, Mehlman CT, Ying J; The epidemiology of neonatal brachial plexus palsy in the United States. J Bone Joint Surg Am. 2008 Jun;90(6):1258-64. doi: 10.2106/JBJS.G.00853.
- Khabyeh-Hasbani N, O'Brien DM, Meisel EM, et al; Current Concepts in Brachial Plexus Birth Injuries: A Comprehensive Narrative Review. Plast Reconstr Surg Glob Open. 2024 Aug 22;12(8):e6083. doi: 10.1097/GOX.0000000000006083. eCollection 2024 Aug.
- Skada på plexus brachialis; H Knipe; Radiopaedia
- Mapping Population-Level Differences in Brachial Plexus Birth Injury: An International Meta-Analysis; H Cordray et al; The Journal of Hand Surgery
- Arslan O, Giray B, Tug N; Obstetric brachial plexus injury: risk factors and clinical follow-up results. J Turk Ger Gynecol Assoc. 2025 Sep 3;26(3):204-211. doi: 10.4274/jtgga.galenos.2025.2025-3-3. Epub 2025 Aug 22.
- Management of Adult Brachial Plexus Injuries; J R Hill et al; The Journal of Hand Surgery
- Pejkova S, Filipce V, Peev I, et al; Brachial Plexus Injuries - Review of the Anatomy and the Treatment Options. Pril (Makedon Akad Nauk Umet Odd Med Nauki). 2021 Apr 23;42(1):91-103. doi: 10.2478/prilozi-2021-0008.
- Review of rehabilitation protocols for brachial plexus injury; H Li et al; Frontiers in Neurology
- Ramachandran M, Eastwood DM; Botulinum toxin and its orthopaedic applications. J Bone Joint Surg Br. 2006 Aug;88(8):981-7.
- Hale HB, Bae DS, Waters PM; Current concepts in the management of brachial plexus birth palsy. J Hand Surg Am. 2010 Feb;35(2):322-31.
- Phrenic nerve transfer in brachial plexus injury; NICE Interventional procedures guidance, Nov 2013
- Free-functioning gracilis transfer to restore upper limb function in brachial plexus injury; Interventional procedures guidance [IPG687]. March 2021.
Om författarenVisa fullständig biografi
Uppdaterad av

Dr Philippa Vincent, MRCGP
Allmänläkare, Medicinsk Författare
MB BS, Bsc, MRCGP (2000), DCH, DFSRH, DRCOG
Dr Philippa Vincent är en NHS-läkare som arbetar i norra London.
Om recensentenVisa fullständig biografi

Dr Toni Hazell, FRCGP
MBBS, BSc, FRCGP, DFSRH, Dip GU med, DRCOG, DCH (London, UK, 2000)
Dr. Toni Hazell tog examen från St. Mary’s Hospital Medical School och genomförde sin VTS vid Northwick Park Hospital.
Artikelhistorik
Artikeln finns också på Engelska, Tyska, Spanska, Franska, Italienska, Portugisiska, Hindi, Hebreiska, Arabiska, och Svenska.
Next review due: 1 Apr 2031
1 Oct 2026 | Senaste versionen
Enkel tillgång till pålitliga behandlingar och hälsotjänster online.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.





Mer inom neurologi
- Akustiska neurom
- Agenes av corpus callosum
- Cauda equina-syndrom
- Komplikationer av HIV-infektion
- Demens med Lewykroppar
- Epilepsi hos vuxna
- Undersökning av kranialnerverna
- Foster Kennedys syndrom
- Interosseös nervkompression
- Lambert-Eaton myasteniskt syndrom
- Limb-gördel muskeldystrofi
- Neurologisk historia och undersökning
- Mardrömsstörning
- Obstruktivt sömnapnésyndrom
- Patogen frilevande amöba
- POEMS syndrome
- Ptos och ögonlocksretardation
- Refsums sjukdom
- Reyes syndrom
- Wernicke-Korsakoff syndrom