Keratoacanthoma
Granskad av Dr Krishna Vakharia, MRCGPSenast uppdaterad av Dr Colin Tidy, MRCGPSenast uppdaterad 23 Nov 2022
Uppfyller patientens redaktionella riktlinjer
- Ladda nerLadda ner
- Dela
- Language
- Diskussion
- Ask Patient
- Ljudversion
- Lägg till i föredragna källor på Google
Medicinska yrkesverksamma
Professionella referensartiklar är utformade för att användas av hälso- och sjukvårdspersonal. De är skrivna av brittiska läkare och baserade på forskningsbevis, brittiska och europeiska riktlinjer. Du kanske hittar en av våra hälsoartiklar mer användbar.
What are keratoacanthomas?
Keratoacanthomas (KAs) are very rapidly growing squamo-proliferative lesions that look like well-differentiated squamous cell carcinomas (SCCs) pathologically. Keratoacanthomas are characterised by rapid growth over a few weeks to months, followed by spontaneous resolution over 4-6 months in most cases.
Keratoacanthomas are benign epidermal growths and not a malignant variant of SCC.1
How common are keratoacanthomas? (Epidemiology)
Incidence is estimated at 1 in 1,000.
Peak incidence occurs in those aged over 60 years. It is rare in young adults.
It is uncommon in darker-skinned patients.
Males are twice as often affected as females.
Epidemiological data are similar to SCC and Bowen's disease in terms of age, sex and the site of lesions.
Riskfaktorer
Sunlight and chemical carcinogens have been implicated.
Trauma, genetic factors and immunocompromised status have also been associated.
Industrial workers exposed to pitch and tar have a higher incidence of both keratoacanthoma and SCC.
Keratoacanthoma symptoms
Typically, rapid growth over a few weeks to months, followed by a slow spontaneous resolution over 4-6 months (but may take up to one year).
Most occur on sun-exposed areas - eg, the face, neck, and dorsum of hands and forearms.
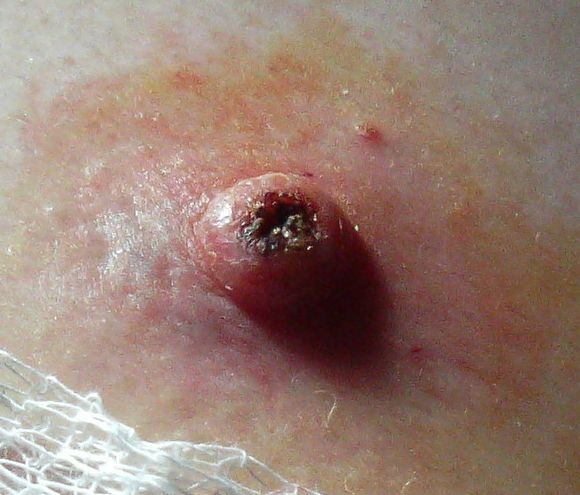
They are usually solitary and begin as firm, round, skin-coloured or reddish papules that rapidly progress to dome-shaped nodules with a smooth shiny surface. A central crater of ulceration may develop, or a keratin plug that may project like a horn.
They leave a residual scar if not excised.
A recent large systematic review has shown that none of the cases of keratoacanthoma from 113 published articles resulted in death or distant metastases. This was compared with 429 cases of SCC of the skin, with 61 cases of metastases and 24 deaths as a direct result of SCC. The authors clearly state that the biological behaviour of the keratoacanthomas and SCCs is distinct and evident.1
Generalised eruptive keratoacanthoma (GEKA) of Grzybowski is a sporadically occurring, extremely rare variant of KA characterised clinically by severely pruritic, generalised eruption of numerous small follicular papules, often with a central keratotic plug, and histologically by typical features of solitary keratoacanthoma.2 .
Keratoacanthoma
Differentialdiagnos3 4
Utredningar
Shave biopsy of keratoacanthoma is indistinguishable from invasive SCC. Therefore, excisional or deep incisional biopsy is required.
A recent study has demonstrated that there is a large regional variation in the diagnosis of keratoacanthoma and SCCs in Great Britain and Ireland.5
This is because microscopic differentiation between these two entities is often problematic, and sometimes impossible.6
Keratoacanthoma treatment and management
As they are hard to distinguish from SCCs, patients with suspected keratoacanthomas should be referred under the two-week waiting system. However, the patient can be reassured that they will not cause harm.
Complete excision is the treatment of choice for all skin lesions thought to be keratoacanthoma.
Medical treatment is reserved for when surgical intervention is not possible - eg, multiple lesions not amenable to surgery because of size or location.
Treatments that have produced some success include systemic retinoids (eg, isotretinoin), intralesional methotrexate, 5-fluorouracil, bleomycin and steroids, and topical imiquimod, and 5-fluorouracil.7 8
Prognos
Prognosis is excellent following excisional surgery. Recurrence after surgical resection is rare.9
Without surgery, prognosis is usually good; however, there is a major controversy over the natural behaviour of KA. keratoacanthomas have been described as benign lesions, but also as variants of SCC.6
Prevention of keratoacanthomas
Patient education in sun-protection is important.
Exklusiva uppdateringar för vårdpersonal
Håll dig informerad med de senaste kliniska uppdateringarna, professionella insikter och evidensbaserad vägledning. Patient Pro-nyhetsbrevet sammanställer viktigt innehåll för vårdpersonal—levererat direkt till din inkorg.
Genom att prenumerera accepterar du våra Sekretesspolicy. Du kan avsluta prenumerationen när som helst. Vi säljer aldrig dina uppgifter.
Vidare läsning och referenser
- Keratoacanthoma; DermNet NZ
- Zito PM, Scharf R; Keratoacanthoma. StatPearls, Aug 2022.
- Keratoacanthoma; Sällskapet för dermatologi inom primärvården.
- Savage JA, Maize JC Sr; Keratoacanthoma clinical behavior: a systematic review. Am J Dermatopathol. 2014 May;36(5):422-9. doi: 10.1097/DAD.0000000000000031.
- Nofal A, Assaf M, Nofal E, et al; Generalized eruptive keratoacanthoma: proposed diagnostic criteria and therapeutic evaluation. J Eur Acad Dermatol Venereol. 2014 Apr;28(4):397-404. doi: 10.1111/jdv.12226. Epub 2013 Aug 6.
- Stefaniak AA, Chlebicka I, Krajewski P, et al; Do Not Judge a Book by its Cover: Masquerading as Keratoacanthoma. Acta Derm Venereol. 2020 Mar 12;100(6):adv00074. doi: 10.2340/00015555-3423.
- Riahi RR, Cohen PR; Malignancies with skin lesions mimicking keratoacanthoma. Dermatol Online J. 2013 Nov 15;19(11):20397.
- Carr RA, Houghton JP; Histopathologists' approach to keratoacanthoma: a multisite survey of regional variation in Great Britain and Ireland. J Clin Pathol. 2014 Apr 24. doi: 10.1136/jclinpath-2014-202255.
- Lammoglia-Ordiales L, Toussaint-Caire S, Contreras-Barrera M, et al; Assessment of syndecan-1 (CD138) and Ki-67 expression for differentiating keratoacanthoma and squamous cell carcinoma. J Drugs Dermatol. 2013 Mar;12(3):e53-8.
- Aubut N, Alain J, Claveau J; Intralesional methotrexate treatment for keratoacanthoma tumors: a retrospective case series. J Cutan Med Surg. 2012 May-Jun;16(3):212-7.
- Plachouri KM, Mulita F, Bousis D, et al; Successful treatment of a keratoacanthoma in a young patient with the application of topical 5% imiquimod cream. Clin Case Rep. 2021 Nov 6;9(11):e04920. doi: 10.1002/ccr3.4920. eCollection 2021 Nov.
- Liu XG, Liu XG, Wang CJ, et al; Lower lip recurrent keratoacanthoma: A case report. World J Clin Cases. 2022 Jul 16;10(20):6960-6965. doi: 10.12998/wjcc.v10.i20.6960.
Om författarenVisa fullständig biografi
Uppdaterad av

Dr Colin Tidy, MRCGP
Allmänläkare, Medicinsk Författare
MBBS, MRCGP, MRCP (Paediatrics), DCH
Dr Colin Tidy är en NHS-läkare, baserad i Oxfordshire.
Om recensentenVisa fullständig biografi

Dr Krishna Vakharia, MRCGP
Medicinsk chef för hälsa, Optum UK
MBChB, MRCGP(2013), BMedSci (hons), DFSRH, DRCOG, PGDipDerm (Distn)
Dr Krishna Vakharia är en NHS-läkare. Hon är också en regelbunden examinator för den postgraduate Diplom i Praktisk Dermatologi vid Cardiff University samt Chief Medical Officer för hälsa på Optum UK.
Artikelhistorik
Artikeln finns också på Engelska, Tyska, Spanska, Franska, Italienska, Portugisiska, Hindi, Hebreiska, Arabiska, och Svenska.
Next review due: 22 Nov 2027
23 Nov 2022 | Senaste versionen
Enkel tillgång till pålitliga behandlingar och hälsotjänster online.
Common conditions
Get help with common conditions through the NHS, without a GP appointment.





Mer inom dermatologi
- Acne vulgaris
- Balanitis
- Basalcellscancer
- Vattkoppor
- Chondrodermatitis nodularis
- Dermatitis artefacta
- Dermatitis herpetiformis
- Discoid (nummulärt) eksem
- Epidermal nevus och dess syndrom
- Erythema induratum
- Erythema multiforme
- Svampinfektioner i naglarna
- Melasma
- Myosit - polymyosit och dermatomyosit
- Necrobiosis lipoidica
- Oral herpes simplex
- Postinflammatorisk hyperpigmentering av huden
- Staphylokockorskalad hudsyndrom
- Trombotisk trombocytopen purpura
- Zinkbrist, överskott och tillskott